
Designed to print on one page, wallet/card size when folded. Pinch to zoom, then drag to move around the card.
MEDICAL INFORMATION CARD
J-POUCH (Ileal Pouch-Anal Anastomosis / IPAA)
What is a J-Pouch?
A surgically created reservoir from the small intestine (ileum) that replaces the colon and rectum. Common reasons include Ulcerative Colitis, FAP, and Indeterminate Colitis, among others. Stool passes through the anus, with no external ostomy.
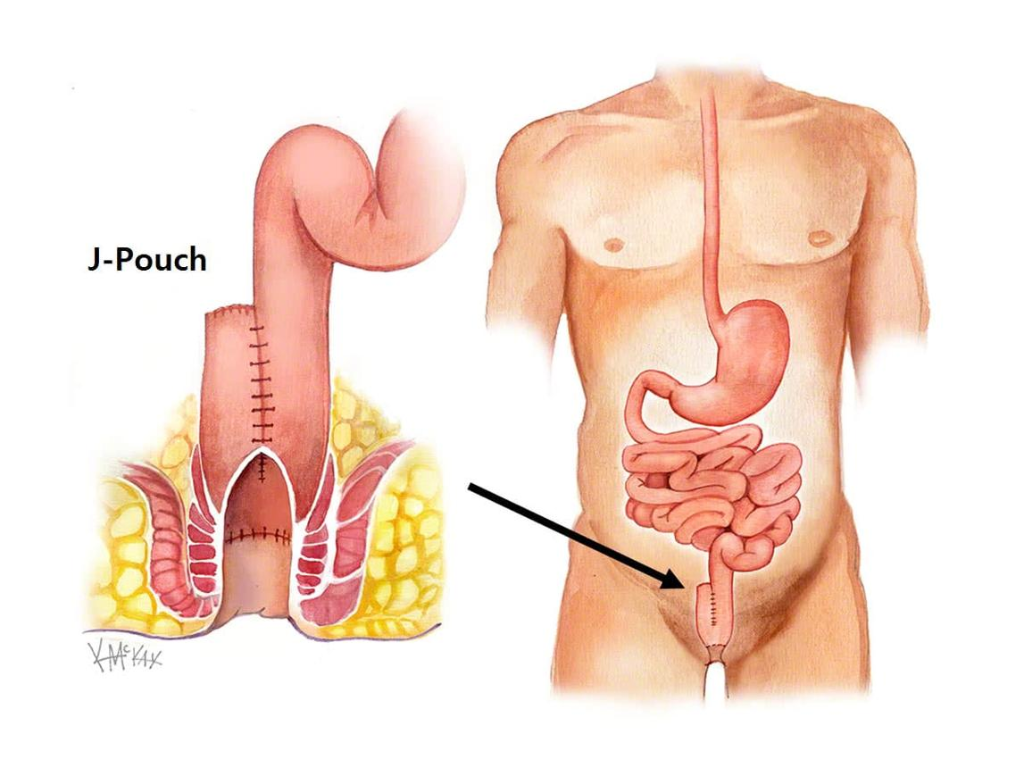
J-pouch anatomy
⚠️ Emergency Signs
Seek urgent medical care for:
- • Possible obstruction: Severe abdominal pain, swelling, vomiting, inability to keep fluids down, or little/no stool or gas output
- • High fever: 39°C / 102°F or higher, especially with abdominal pain
- • Dehydration: Dry mouth, intense thirst, dark or reduced urine, dizziness, confusion, weakness, body pain, nausea, headache, muscle cramping
Key Medical Notes
Hydration & Electrolytes
No colon = reduced water/electrolyte absorption. Expect 6 to 12+ BMs/day. Higher risk of dehydration, low sodium & potassium.
Pouchitis
Most common complication, inflammation of the pouch. Sx: urgency, frequency, cramping, fever, bleeding. Commonly treated with ciprofloxacin or metronidazole, or both.
Blockage / Obstruction
Prior surgeries increase adhesion risk. Sx: cramping, bloating, nausea, vomiting, no stool output. Higher risk than average.
Medication Absorption
Faster transit may reduce absorption, especially extended or sustained-release formulations. Prefer standard-release. Consult pharmacist familiar with J-pouch physiology.
Pouchoscopy (not Colonoscopy)
No colon present. Colonoscopy is not applicable. Endoscopic evaluation is called a pouchoscopy. Requires experience with pouch anatomy, use gentle technique.
For informational purposes only. Carry during all healthcare encounters.
Created by A J-pouch is a Journey… with Pit Stops